
Pancreatic Cancer
Pancreatic Cancer: What Should Be Checked Before Symptoms Become Advanced?
Pancreatic cancer can start deep inside the abdomen and may not cause clear symptoms early. This page explains warning signs, risk factors, jaundice, new-onset diabetes, CA 19-9, pancreas-protocol imaging, EUS, biopsy, staging, genetic testing, and treatment planning.
What Is Pancreatic Cancer?
Pancreatic cancer is a malignant disease that starts in the pancreas. The pancreas sits behind the stomach and helps with digestion and blood sugar control. Most pancreatic cancers begin in exocrine cells that help produce digestive enzymes. Pancreatic ductal adenocarcinoma is the most common type. Other tumors, such as pancreatic neuroendocrine tumors, follow different clinical pathways. This distinction matters because diagnosis, staging, and treatment choices can differ. Doctors evaluate tumor type, location, spread, symptoms, nutrition, and general health together. A single diagnosis label cannot describe every pancreatic cancer case.
Why Can Pancreatic Cancer Be Difficult to Detect Early?
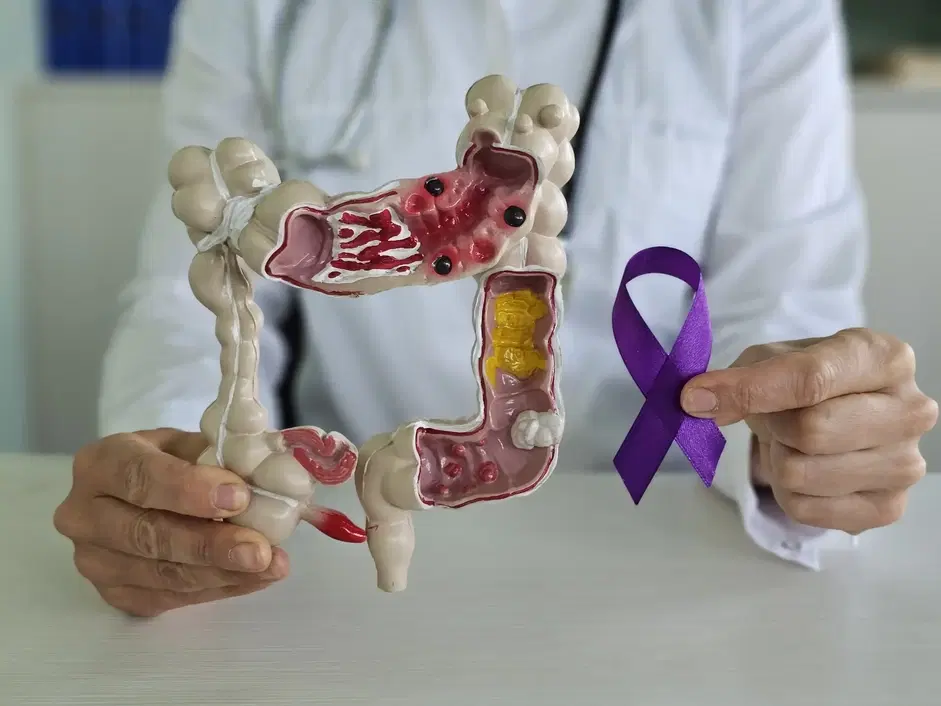
Pancreatic cancer can be difficult to detect early because the pancreas lies deep inside the abdomen. Small tumors usually cannot be felt during routine examination. Early symptoms may look like common digestive problems. Back pain, bloating, appetite change, or fatigue can have many causes. Tumors in different pancreas regions may cause different signs. A tumor in the head may block bile flow sooner. A tumor in the body or tail may stay silent longer. This is why persistent, unexplained, or worsening symptoms need medical assessment.
Which Pancreatic Cancer Symptoms Should Prompt Medical Evaluation?
Jaundice, unexplained weight loss, persistent upper abdominal pain, or new digestive changes should prompt medical evaluation.
Yellow skin, dark urine, pale stool, or itching may suggest bile duct blockage.
Upper abdominal pain may spread toward the back and persist.
Loss of appetite, nausea, vomiting, or unexplained weight loss can develop.
Greasy stools, diarrhea, or worsening blood sugar control may need review.
These symptoms do not always mean pancreatic cancer. Gallstones, hepatitis, ulcers, pancreatitis, and other conditions can look similar. A clinician can decide which tests are appropriate.
Why Is Painless Jaundice an Important Warning Sign?
Painless jaundice is important because a pancreas-head tumor can block bile flow without early pain. Bile normally drains from the liver through ducts into the intestine. A tumor near the bile duct can narrow or block that path. This may cause yellow skin, dark urine, pale stool, and itching. Many pages mention jaundice but skip the anatomy behind it. The location of the tumor explains why symptoms can appear before severe abdominal pain. Jaundice still has many possible causes. It needs prompt medical evaluation rather than self-diagnosis.
Which Risk Factors Matter Beyond Age and Smoking?
Pancreatic cancer risk can involve inherited factors, pancreatitis, diabetes, body weight, and family history.
Chronic pancreatitis can increase risk, especially when inflammation continues for years.
A strong family history may suggest inherited susceptibility in selected families.
New-onset diabetes after age 50 can sometimes be a warning context.
Obesity and long-term type 2 diabetes may contribute to overall risk.
Risk factors do not confirm cancer. They help doctors decide whether symptoms, family history, imaging, genetic counseling, or specialist review need closer attention.
Why Can New-Onset Diabetes Matter in Pancreatic Cancer?
New-onset diabetes can matter because pancreatic cancer can affect insulin-producing function in some patients. Diabetes is common and usually has non-cancer causes. However, sudden diabetes in an older adult may need context-based evaluation. Concern increases when diabetes appears with weight loss, jaundice, abdominal pain, or appetite loss. This does not mean every new diabetes diagnosis needs cancer testing. It means clinicians should connect metabolic changes with the whole symptom pattern. This nuance is often missing from competitor pages. It can help readers avoid both panic and dismissal.
Why Is CA 19-9 Not Enough to Diagnose Pancreatic Cancer?
CA 19-9 is not enough because it can rise in non-cancer conditions and miss some cancers. Bile duct blockage, pancreatitis, liver disease, and other cancers can increase CA 19-9. Some people do not produce this marker reliably. A normal result therefore cannot safely exclude pancreatic cancer. An elevated result cannot confirm it alone. Doctors use CA 19-9 with imaging, symptoms, biopsy results, and treatment context. It may help monitor selected diagnosed patients. It should not replace pancreas-focused imaging or specialist assessment when clinical concern remains.
How Do CT, EUS, and Biopsy Help Confirm the Diagnosis?
CT, EUS, and biopsy help define the tumor, assess spread, and confirm the diagnosis when tissue is needed. Pancreas-protocol CT can show tumor size, vessel contact, and possible spread. MRI may help when CT findings need more detail. Endoscopic ultrasound can examine the pancreas closely from inside the digestive tract. It can also guide tissue sampling. Biopsy helps pathologists identify cancer type. Sometimes tissue is especially important before chemotherapy or radiation. Doctors balance diagnostic value, procedure risks, imaging clarity, and treatment goals before choosing the next test.
How Do Stage and Resectability Affect Treatment Planning?
Stage and resectability affect treatment planning by showing whether cancer appears removable and how far it spread. Doctors assess the tumor, lymph nodes, distant organs, and nearby blood vessels. Resectable disease may be approached differently from borderline resectable, locally advanced, or metastatic disease. Vessel involvement can change surgical planning. This detail often receives too little attention in basic articles. Treatment may start with surgery in selected cases. Other cases may need chemotherapy, chemoradiation, systemic therapy, procedures for blockage, or supportive care first. The plan must fit both tumor behavior and patient health.
Why Can Germline and Tumor Testing Be Important?
Germline and tumor testing can be important because inherited and acquired mutations may affect care options. Germline testing looks for inherited variants that may affect the patient and relatives. Tumor testing looks for changes inside the cancer cells. These tests may identify selected treatment considerations, including PARP inhibitor or immunotherapy relevance in defined settings. Results do not guarantee a specific response. Testing decisions depend on cancer type, stage, tissue availability, family history, and local practice. Genetic counseling can help explain family implications. This information supports more precise, evidence-based planning.
Which Treatment Options May Be Discussed for Pancreatic Cancer?
Treatment options may include surgery, chemotherapy, radiation therapy, targeted therapy, immunotherapy, procedures, or supportive care. The plan depends on stage, resectability, biomarkers, symptoms, nutrition, pain, and general health. Surgery may be discussed when disease appears removable and the patient is suitable. Chemotherapy may be used before or after surgery in selected cases. Advanced disease may require systemic treatment and symptom-focused care. Procedures may relieve bile duct or stomach outlet blockage. Supportive care can address pain, digestion, weight loss, and treatment effects. A specialist team should explain goals, limits, alternatives, and follow-up.
When Should Medical Advice Not Be Delayed?
Medical advice should not be delayed when jaundice, persistent pain, unexplained weight loss, or ongoing vomiting occurs. Dark urine, pale stool, itching, fever, or worsening weakness also need review. People with strong family history should discuss risk assessment before symptoms appear. Sudden diabetes with weight loss or abdominal symptoms deserves timely medical attention. Online information cannot diagnose pancreatic cancer or exclude it safely. A doctor can connect symptoms, risk factors, blood tests, imaging, and pathology results. This approach reduces uncertainty and supports appropriate next steps.
References
National Cancer Institute — Pancreatic Cancer Treatment PDQ: https://www.cancer.gov/types/pancreatic/hp/pancreatic-treatment-pdq
American Cancer Society — Signs and Symptoms of Pancreatic Cancer: https://www.cancer.org/cancer/types/pancreatic-cancer/detection-diagnosis-staging/signs-and-symptoms.html
American Cancer Society — Tests for Pancreatic Cancer: https://www.cancer.org/cancer/types/pancreatic-cancer/detection-diagnosis-staging/how-diagnosed.html
American Cancer Society — Can Pancreatic Cancer Be Found Early?: https://www.cancer.org/cancer/types/pancreatic-cancer/detection-diagnosis-staging/detection.html
American Cancer Society — Pancreatic Cancer Risk Factors: https://www.cancer.org/cancer/types/pancreatic-cancer/causes-risks-prevention/risk-factors.html
ASCO — Selection of Germline Genetic Testing Panels in Patients With Cancer: https://ascopubs.org/doi/10.1200/JCO.24.00662
ASCO — Metastatic Pancreatic Cancer Guideline Update: https://pmc.ncbi.nlm.nih.gov/articles/PMC12974607/
T.C. Sağlık Bakanlığı — Sağlık Hizmetlerinde Tanıtım ve Bilgilendirme Faaliyetleri Hakkında Yönetmelik: https://antalyaism.saglik.gov.tr/TR-366500/saglik-hizmetlerinde-tanitim-ve-bilgilendirme--faaliyetleri-hakkinda-yonetmelik.html
T.C. Sağlık Bakanlığı — Uluslararası Sağlık Turizmi ve Turistin Sağlığı Hakkında Yönetmelik: https://adiyamaneah.saglik.gov.tr/EN-419655/regulation-on-international-health-tourism-and-tourist-health.html